

The timing of South Africa’s Corona Virus 2019 (Covid) lockdowns typically lagged the peaks of the disease and didn’t abate during periods of low transmission. In this post, I argue that under the information about the disease available at the time, South Africa’s lockdown policy was irrational,1 even considering only proximal deaths caused by infection. As South Africa followed similar pandemic policy to many countries, South Africa provides a case study to analyse several important aspects of public health policy.
Second, I argue that the effects of wealth on health suggest that South Africa’s lockdown severity likely led to a reduction in total Quality Adjusted Life Years. As South Africa is a country with considerable pre-Covid poverty, these policies likely caused significant further impoverishment. I speculate that the reason for these policy failures was inadequate consideration of the behavioural and economic aspects of public health. I begin with a macro exploration of lockdown stringency using cross-country evidence.
Background
Many of the most stringent lockdowns in the world were in developing countries. South Africa’s average level of lockdown was above the global average. Prima facie, one might expect that the poorer a nation, the less it can afford the economic damage that lockdowns inflict. A countervailing consideration might be that poorer countries have lower health system capacity and thus must resort to non-pharmaceutical interventions. Or that, as with South Africa, poorer nations have higher rates of pre-existing conditions, such as HIV, which might have been expected to increase the lethality of Covid.2 A last and countervailing consideration—poorer countries are often younger, which decreases the mortality of Covid, although this was not known at the time.
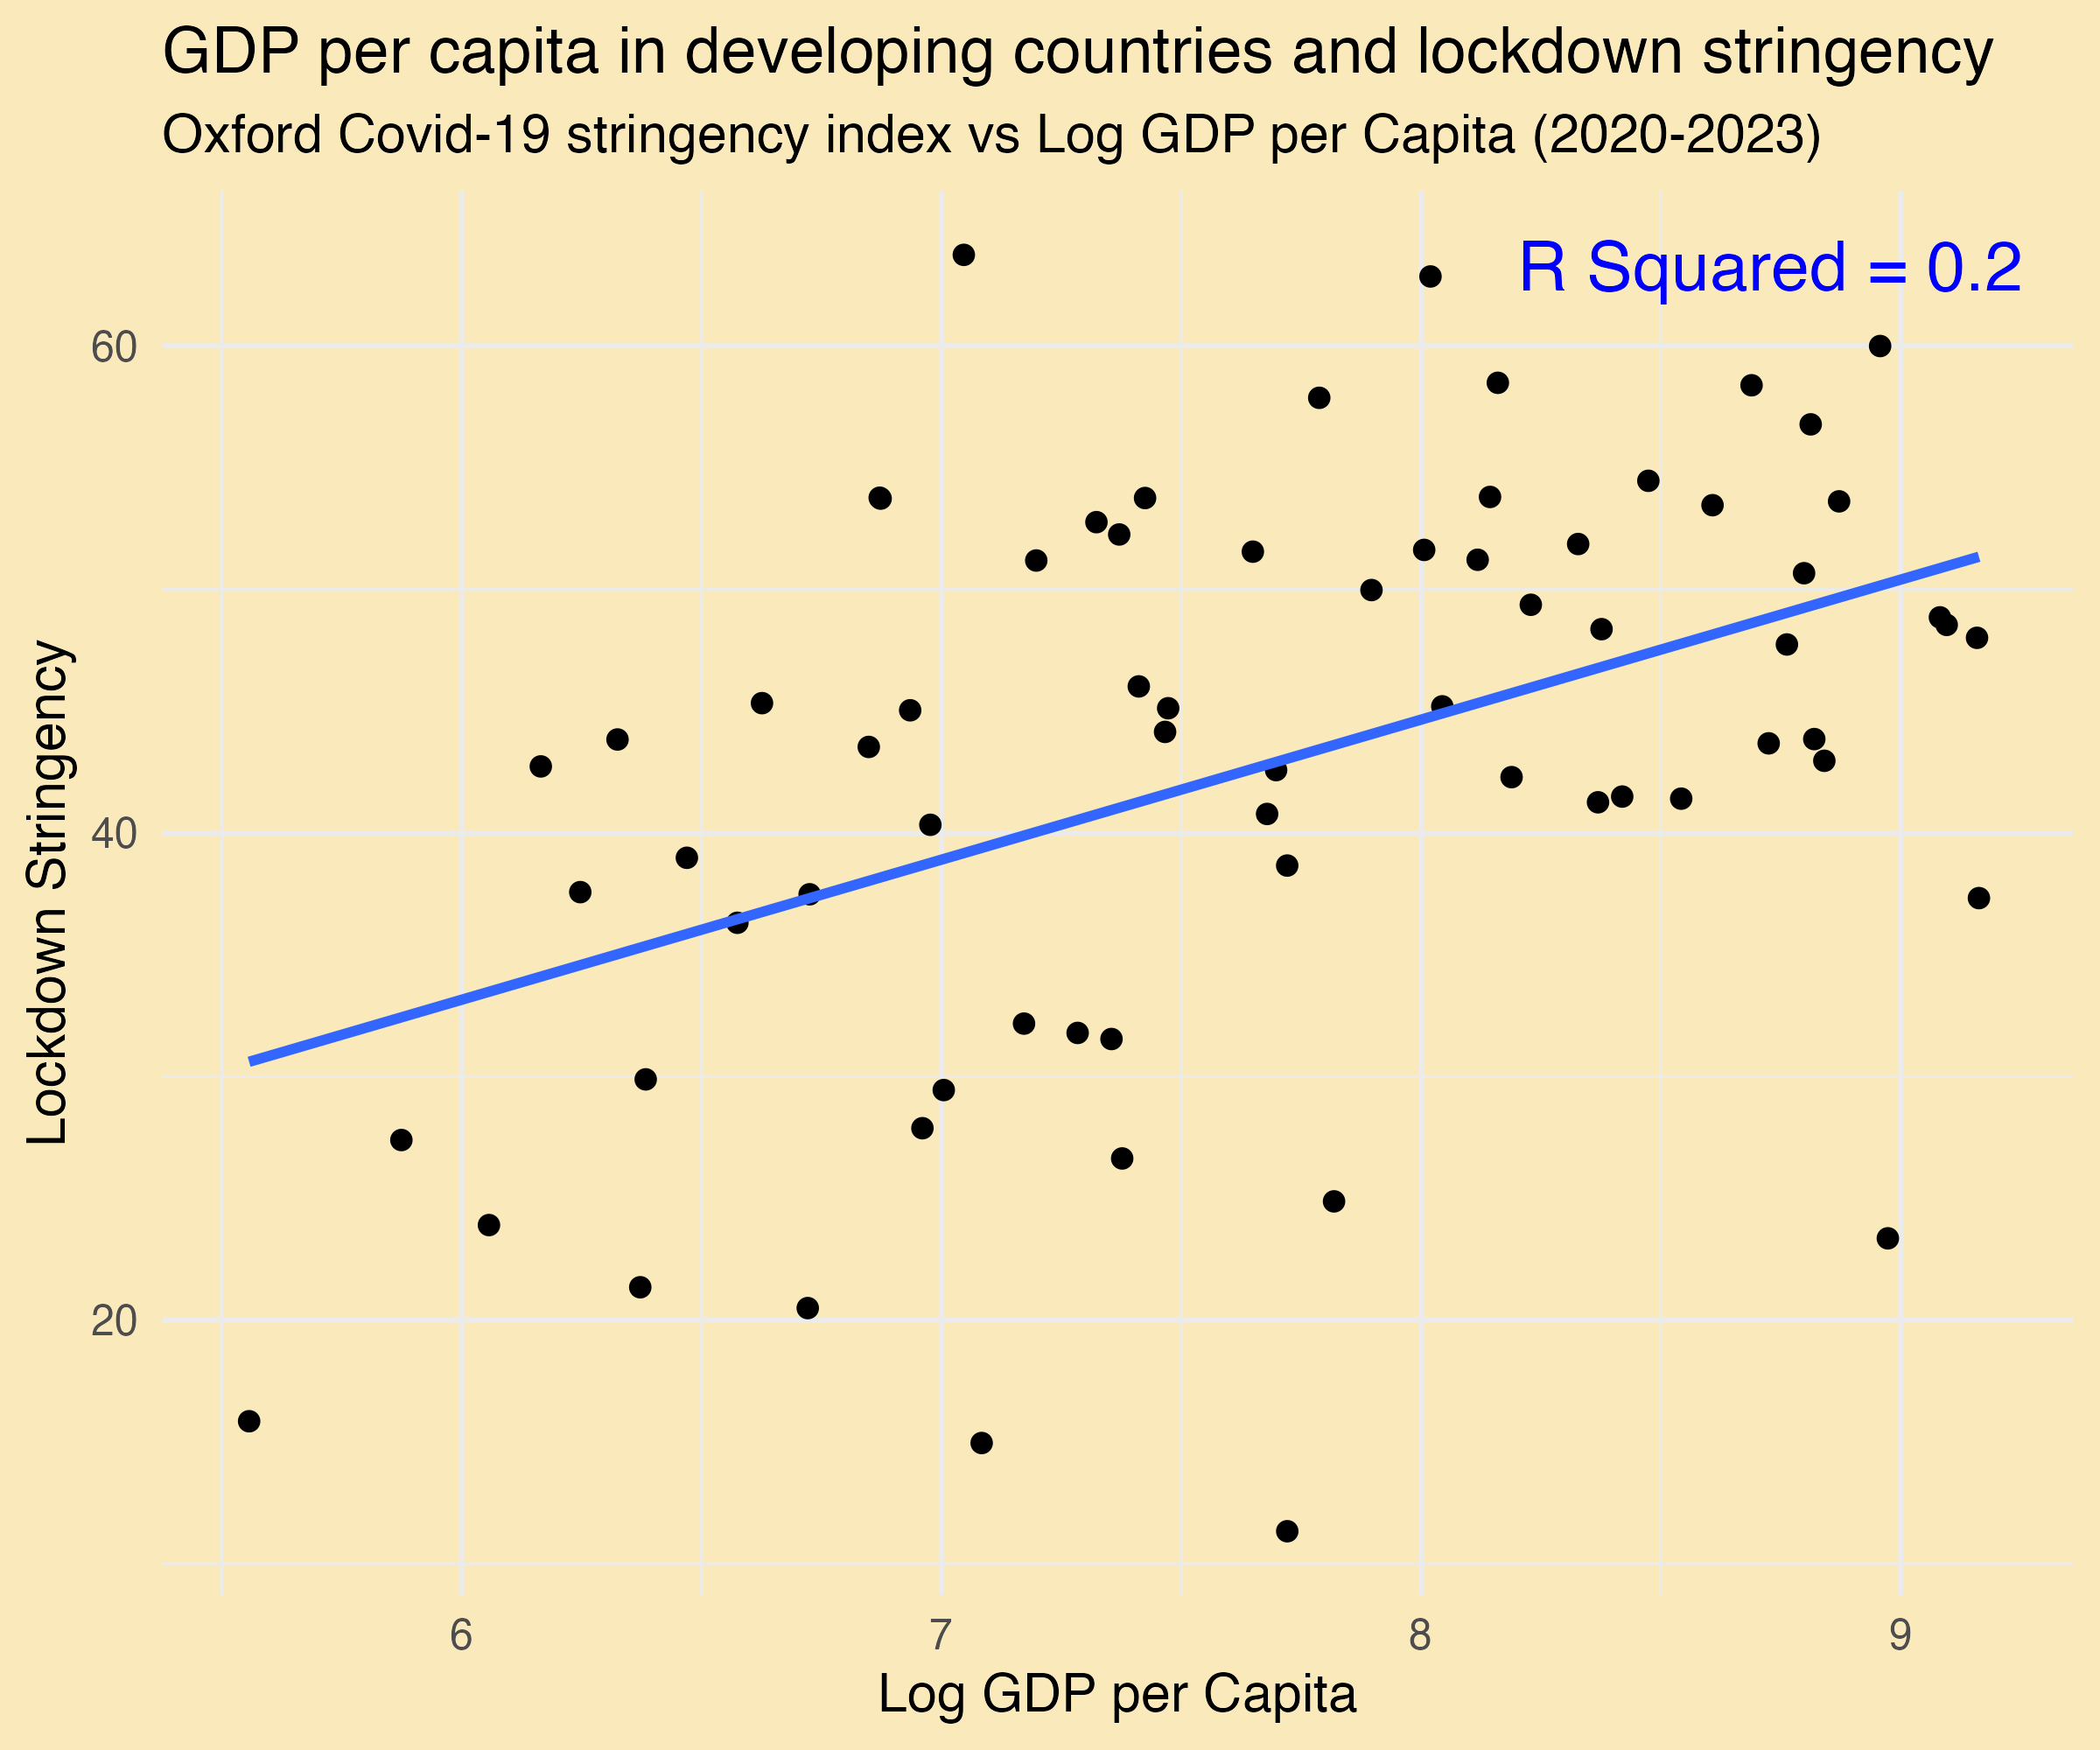
In Figure 1 we can see that for Low- and Middle-Income Countries, the richer the country, the greater the stringency level, perhaps as poorer countries believed they could not afford the costs of lockdowns (Hale et al., 2021). Interestingly, when high-income countries are included in the sample, the correlation disappears.
Figure 13
Interestingly, there is no correlation between a country's lockdown severity and its degree of democracy (calculation from The Economist Intelligence Unit's (2020) Democracy Index). The disregard for human rights in authoritarian regimes was thought to facilitate stricter lockdowns, and this was certainly true for countries such as China. Indeed, South Africa’s Constitutional Court ruled that many of South Africa’s lockdown measures unconstitutionally restricted people’s rights (Davis, 2020). That there is no cross-country regularity to this suggests that epidemiological or economic considerations tended to overwhelm any disregard for human rights or authoritarian consolidation under the guise of pandemic response.
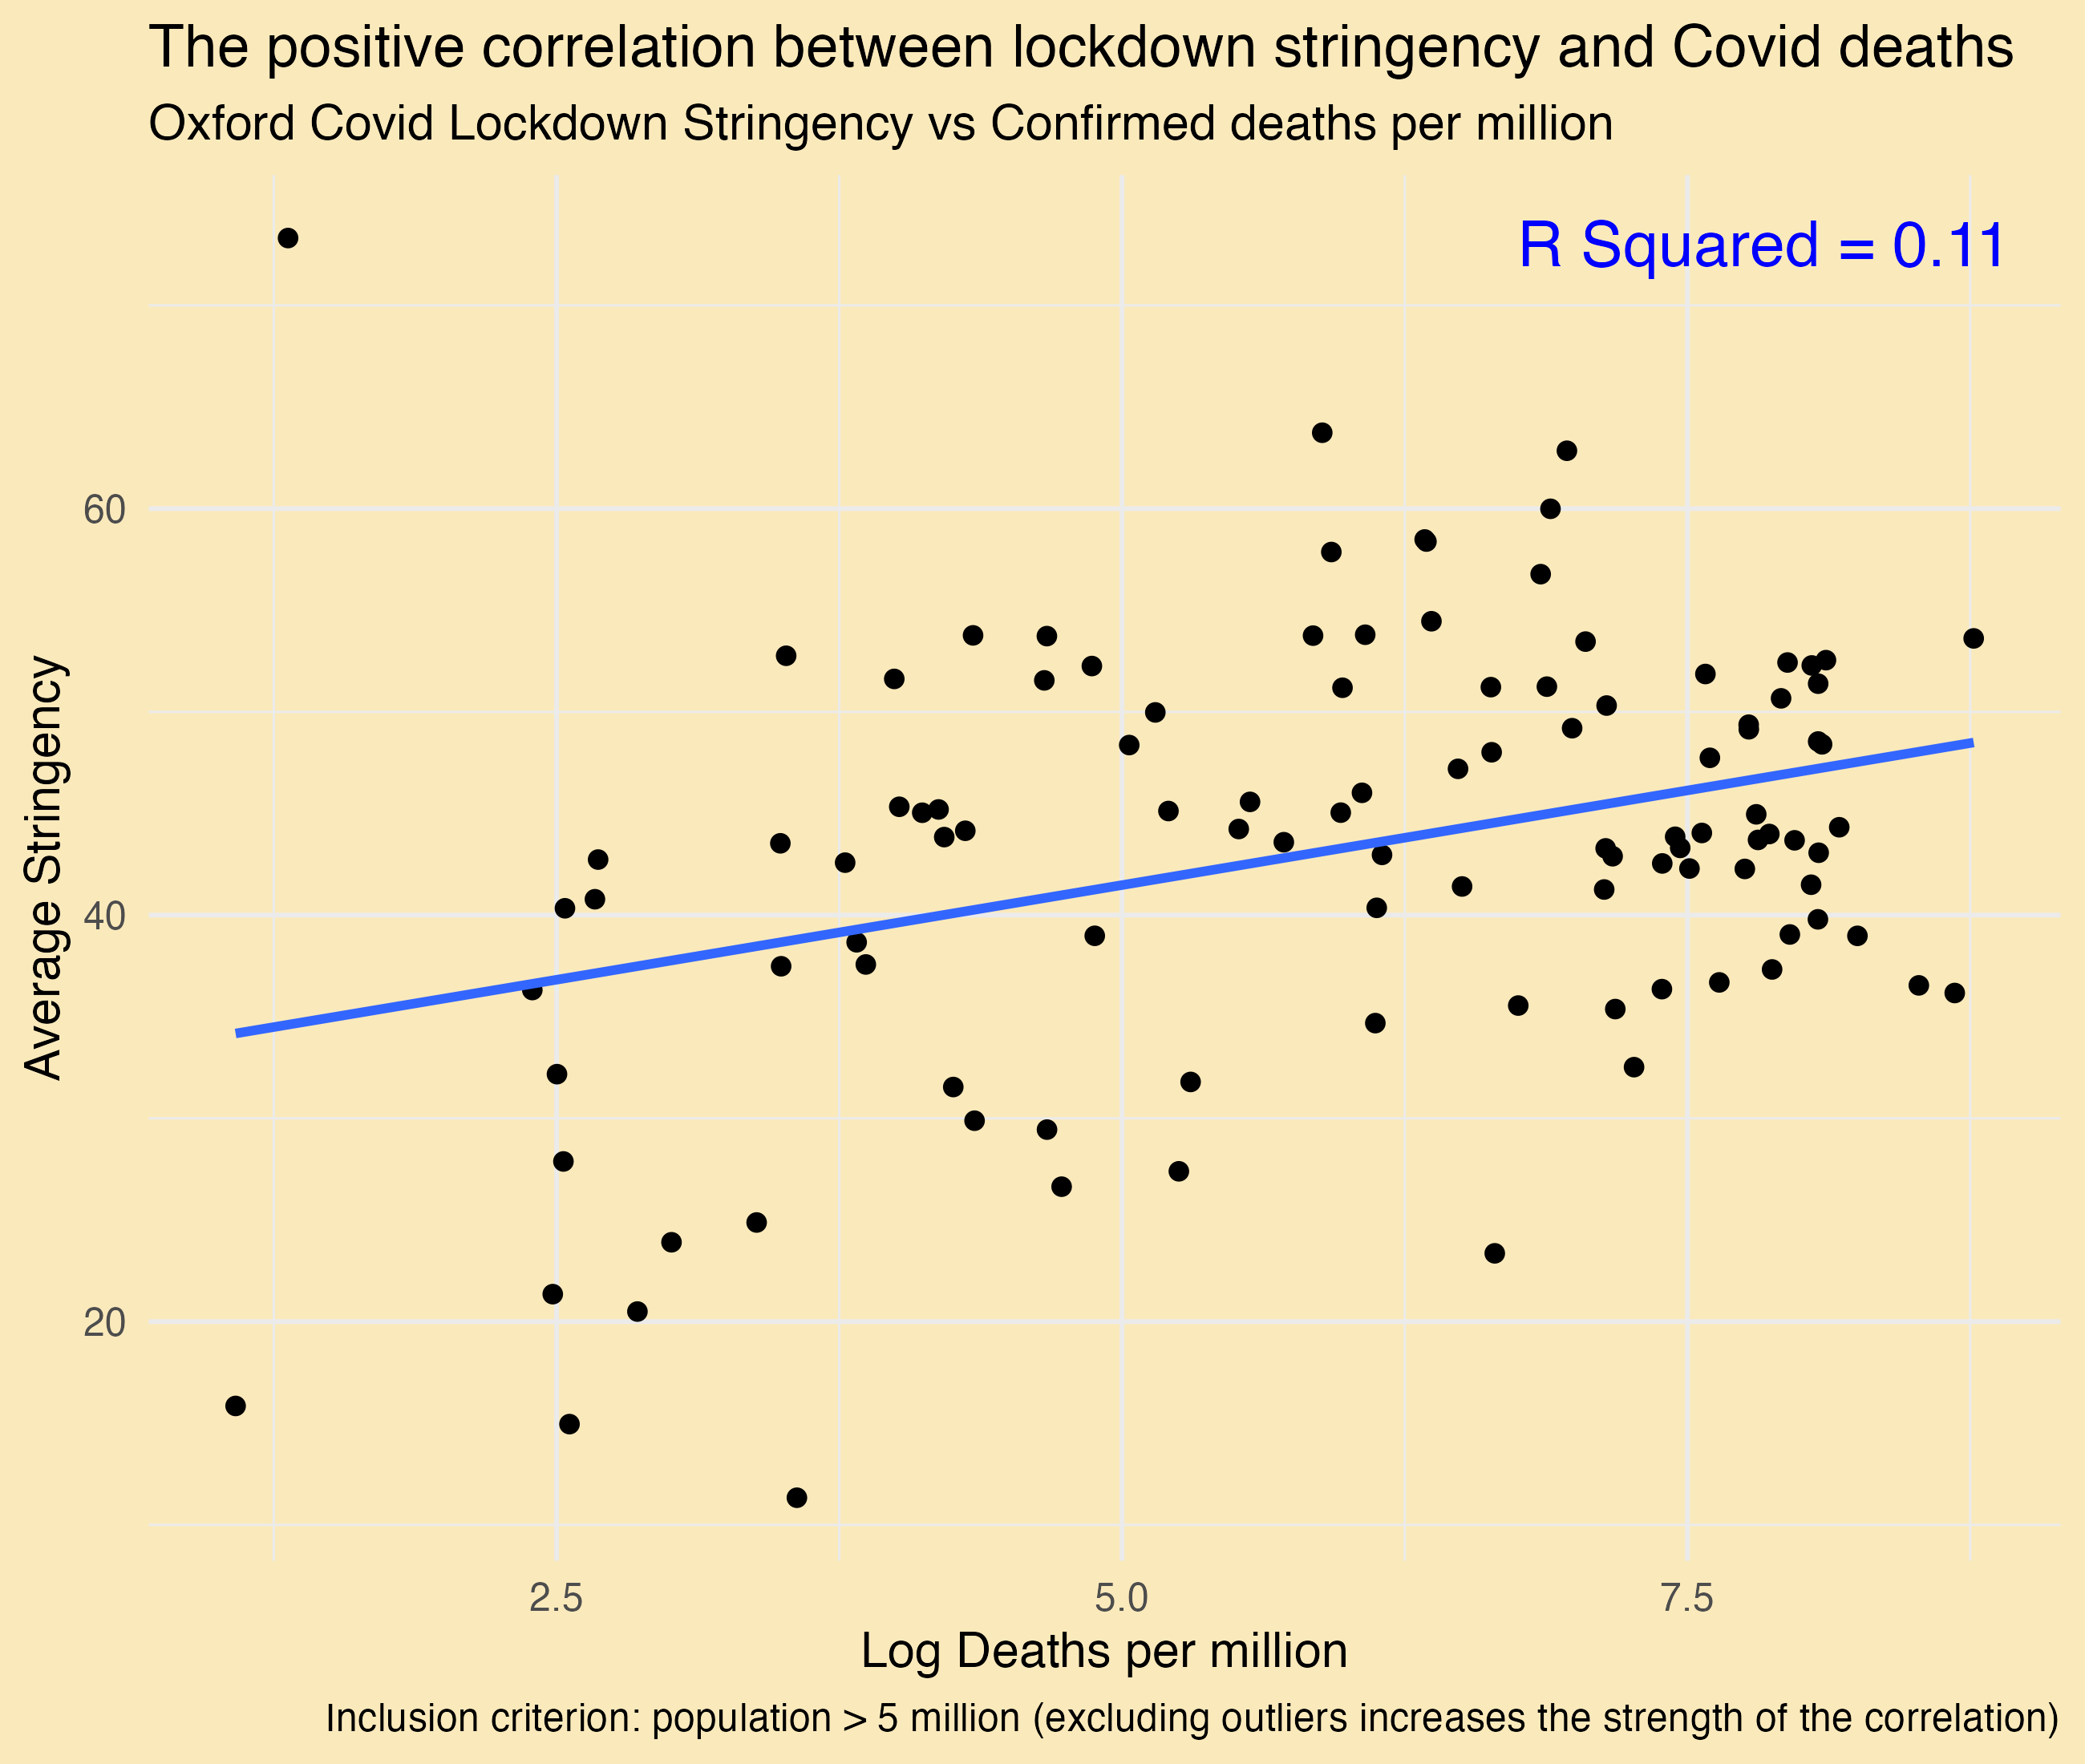
If lockdown stringency substantially reduced deaths, one might expect to see this negative relationship in a cross-section of all countries. However, the opposite is true (see Figure 2). There are many plausible reasons for this. For example, countries with higher comorbidities, or richer & older populations, or lower healthcare capacity may have increased their lockdown severity in response to higher (expected) death rates. However, the best econometric evidence does not support a causal reduction in deaths from lockdowns (see Herby et al., (2022) for a meta-analysis of the best econometric evidence).
Figure 2
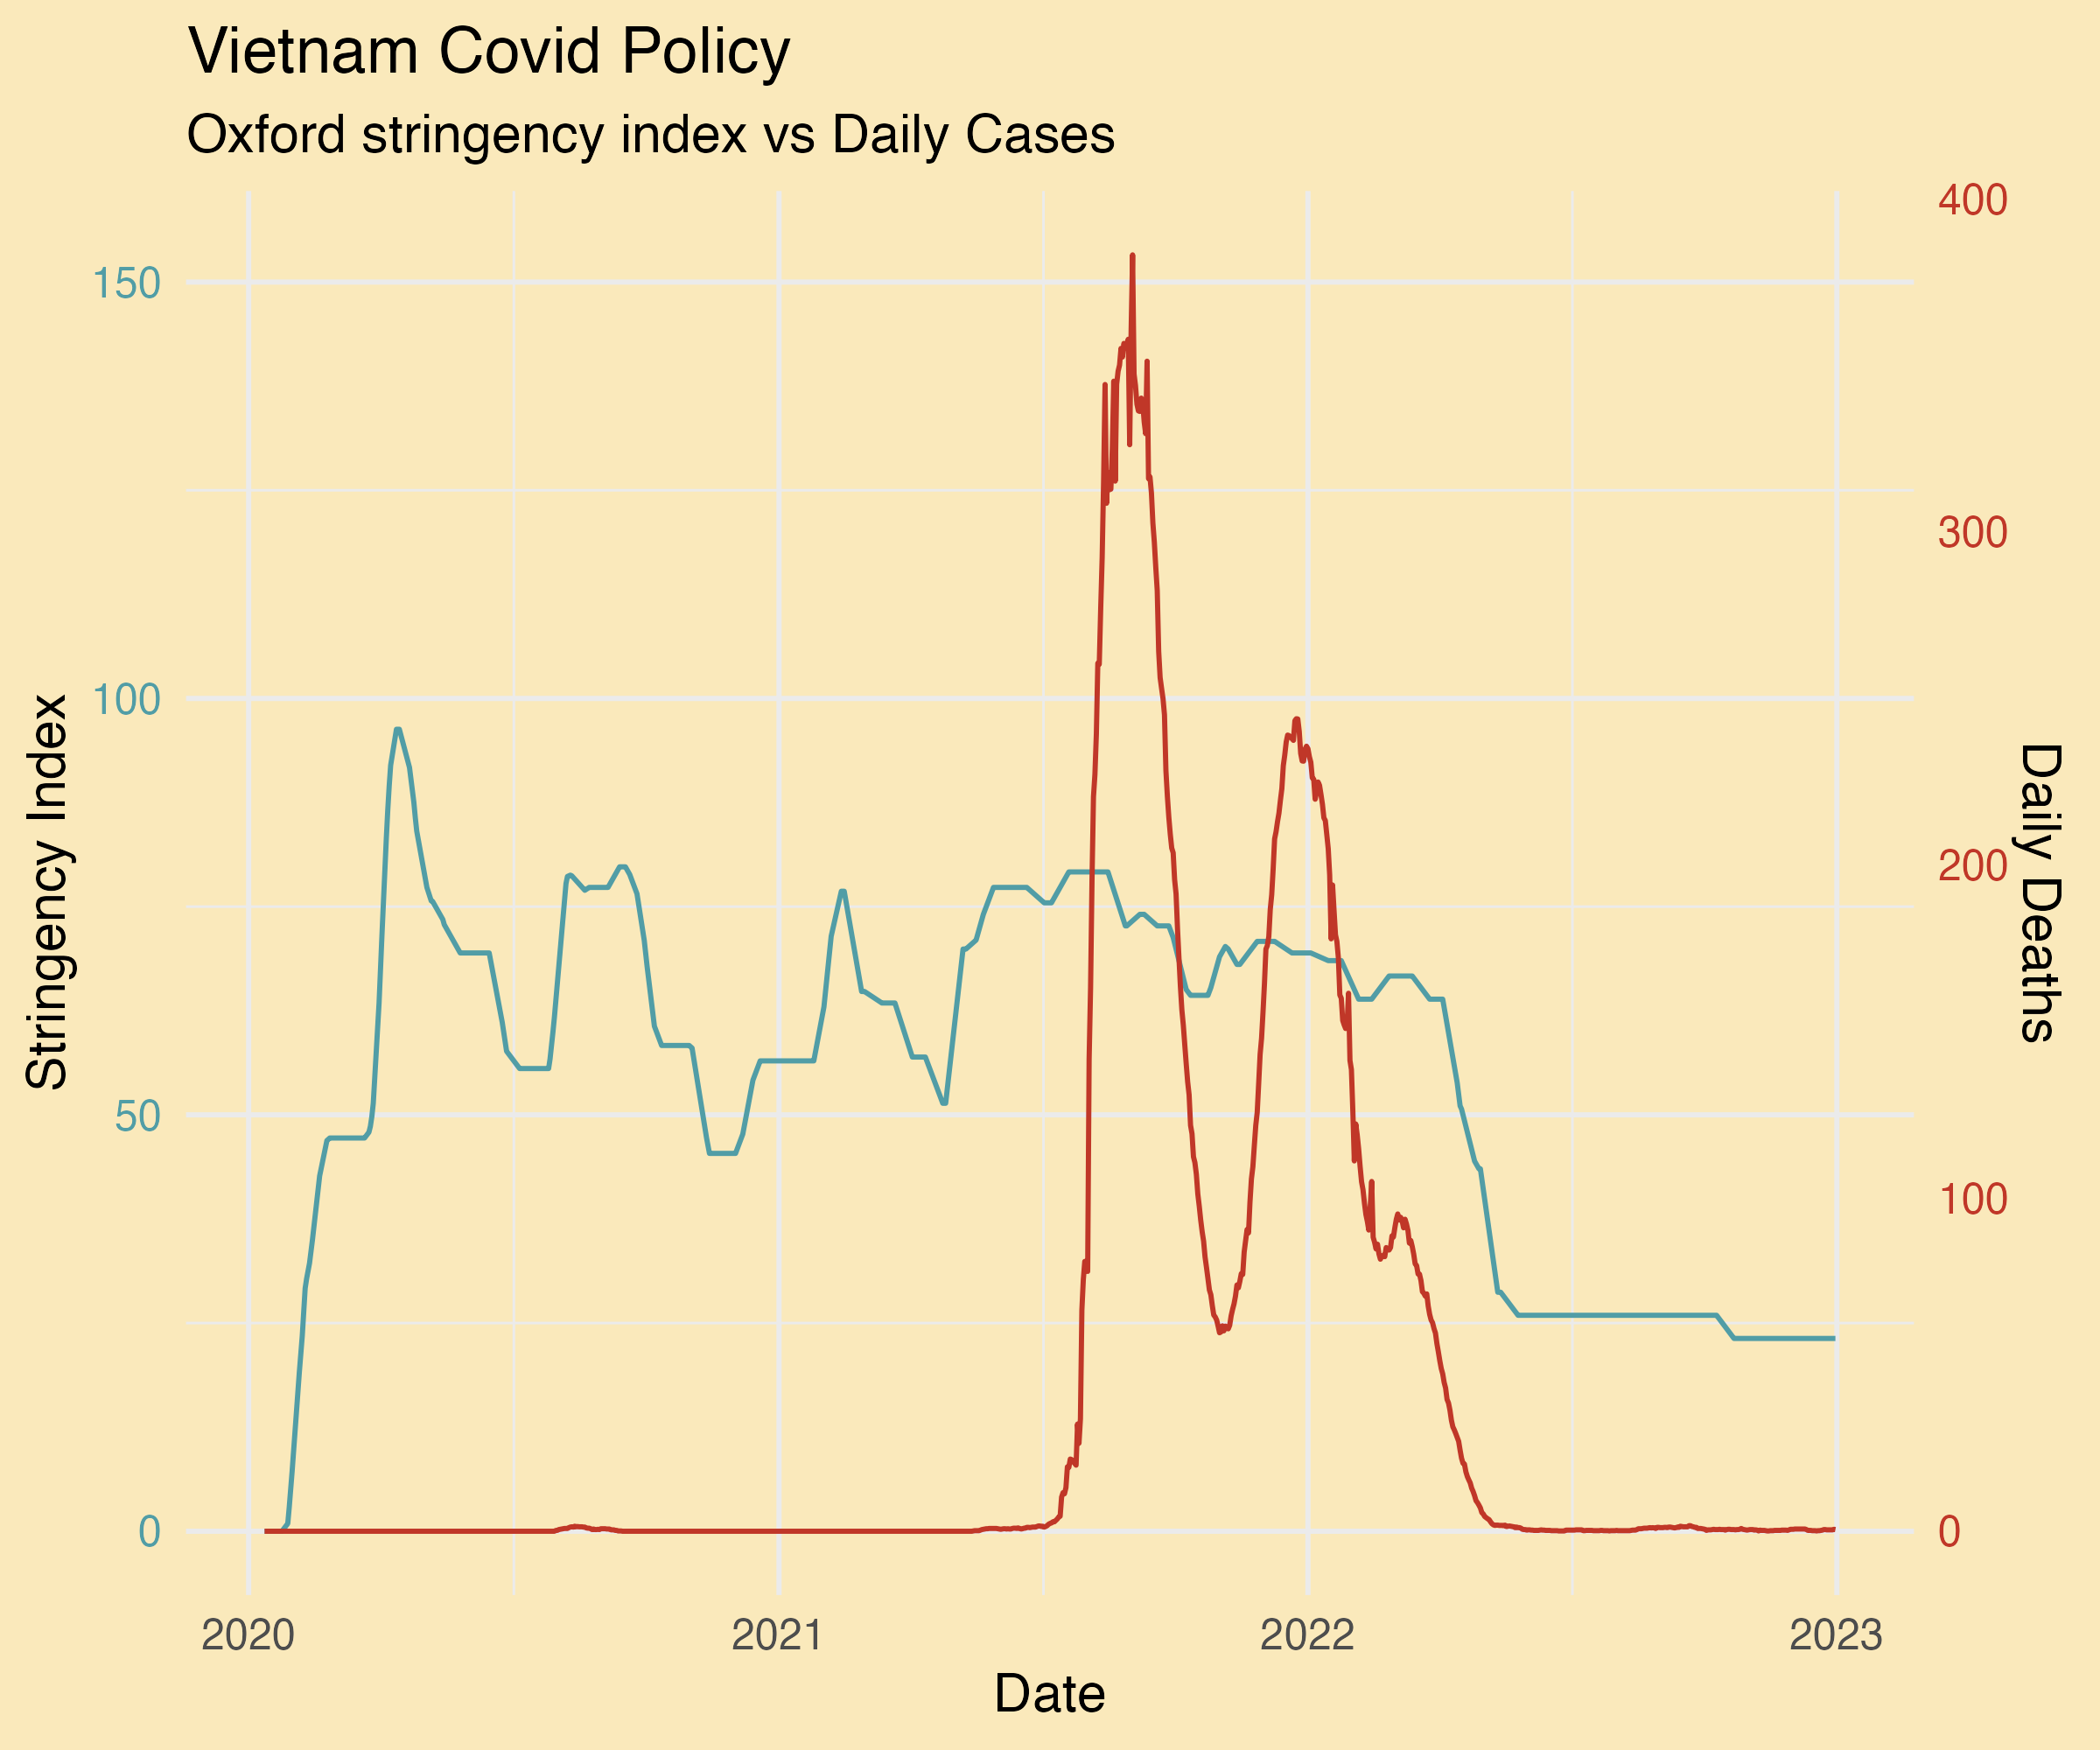
Of course, causal empirical evidence was not available to policymakers at the time. First-principles decisions needed to be made. At first, it was believed that lockdowns could push Covid’s R0 under 1 and thus extinguish the disease before it became endemic. This appeared successful in some “miracle countries” that had previously dealt with respiratory pandemics before, notably Vietnam, China, and South Korea. However, even these countries eventually let the pandemic run its course and Covid deaths to climb (see Figure 3). This was nonetheless an effective strategy only because it allowed for sufficient delay for vaccines to be developed and populations vaccinated.
Figure 3
These early international successes led many countries, including South Africa, to implement extremely stringent lockdowns at first. However, it was evident very early on that most countries would not be able to extinguish Covid transmission, including within weeks in South Africa. The remainder of this essay considers what a rational Covid lockdown policy would have looked like under the information available at the time.
Optimum lockdown policy
Empirical evidence is more persuasive on the effect of lockdowns than any modelling exercise, and as has been discussed, many studies have concluded that lockdowns were not successful (Herby et al., 2022). Yet, I argue that a model relying on the most reasonable assumptions at the time shows that South Africa’s lockdowns were irrational. This is not merely an academic exercise, overreliance on epidemiological models and medical-expert-led policymaking led to policy mistakes that should be avoided going forward. Indeed, the South African Presidency’s favoured epidemiological model forecasted 10x more deaths than actually occurred (Davids et al., 2023). Further, the model assumed more stringent lockdowns than actually occurred, further showing how poorly calibrated the model was, which in turn likely led to more restrictive lockdown measures than had there been more sophisticated Covid models.
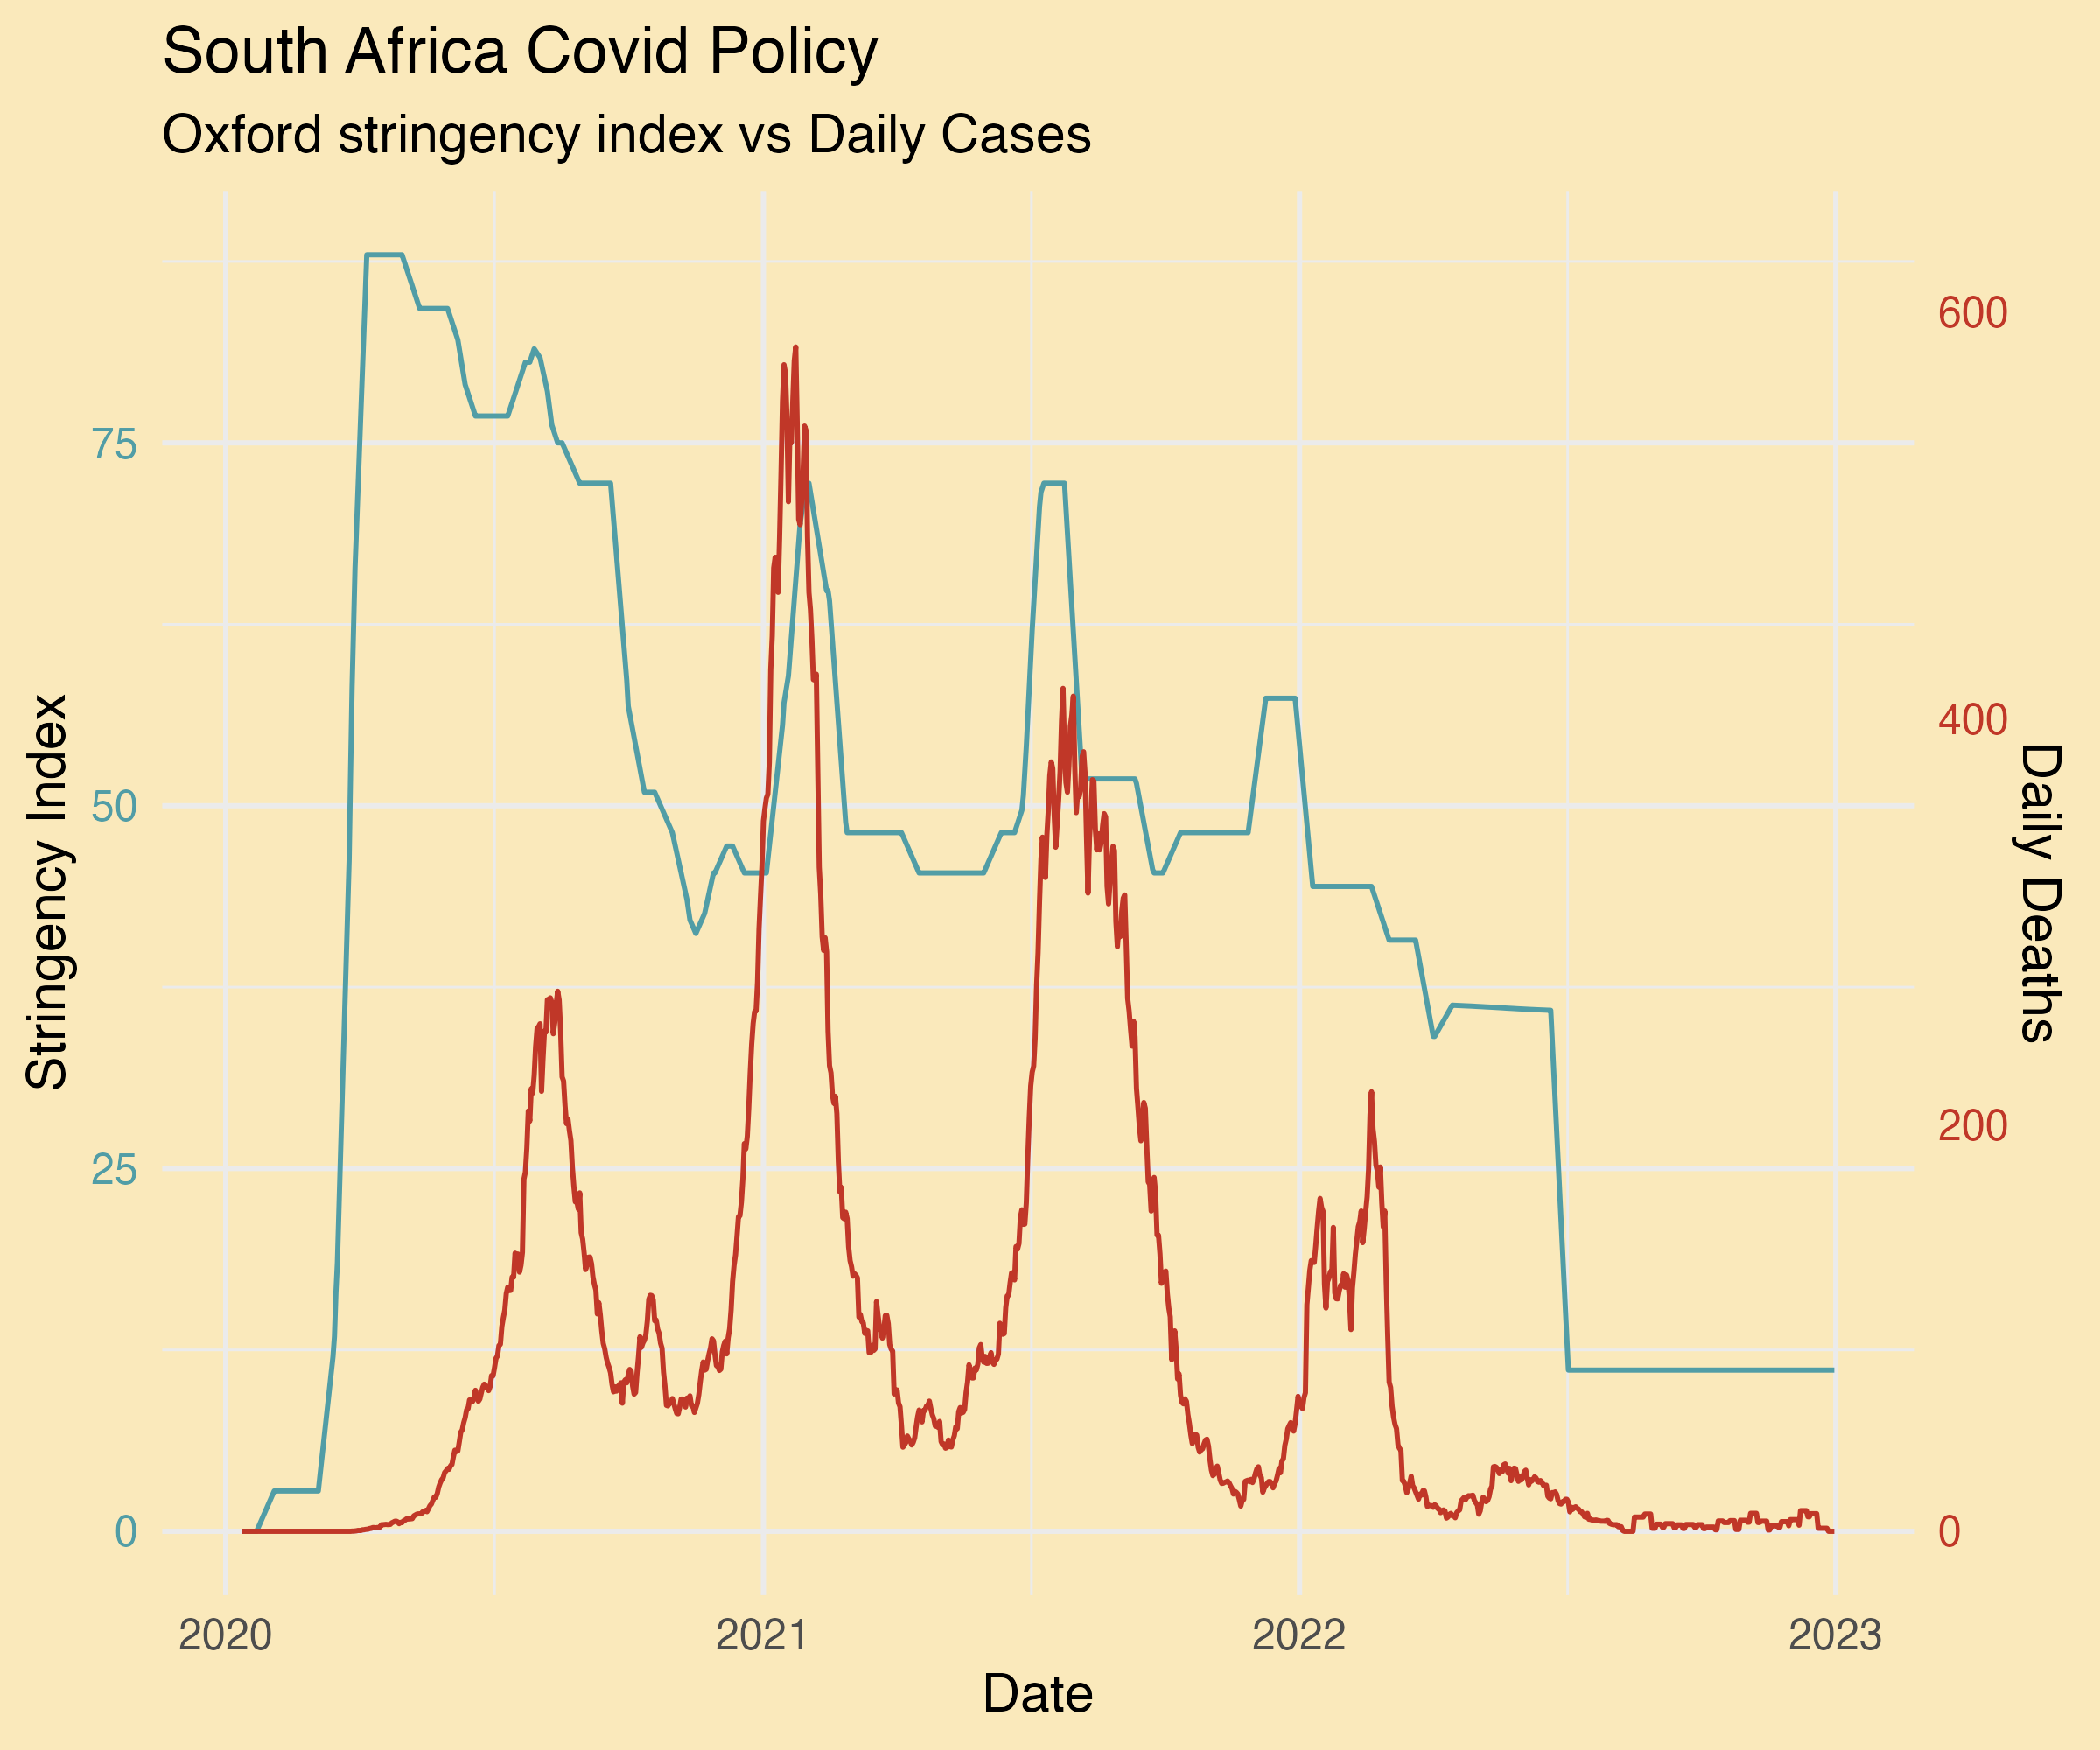
Instead, I argue that lockdowns should have been completely lifted between waves, with reimplementation at the first sign of exponentiating transmission. As can be seen in Figure 4, lockdown intensity often lagged infection exponentiation and lockdown stringency never dropped below 40 until the end. The aim should have been to keep hospitalisations as flat as possible throughout the pandemic. I begin with some of the key assumptions needed to come to this conclusion before a deeper analysis of this optimum lockdown policy.
Figure 4
Assumptions and implications for optimum Covid policy
Lockdowns cannot reduce R0 below 1. Although this assumption was not true for the handful of miracle nations described above, it was true for most, and it was obviously going to be true for South Africa. Many South Africans live in large households where disease isolation is functionally impossible, people need to go to work to survive, and government capacity is generally very low.
Lockdowns can reduce R0. This assumption simply states that lockdowns had some effect. This was a reasonable assumption for the time, and the empirical evidence supports this assumption (Alfano and Ercolano, 2020). This assumption entails that lockdowns had two effects. First, there is a timing effect: lockdowns slow down waves prolonging the time to their peak. And a point-in-time magnitude effect: lockdowns effectively “flattened the curve”, decreasing the amplitude of the waves’ peaks.
Only herd immunity ends Covid waves. Importantly, what the above reduction in R0 does not show is that lockdowns can reduce the total number of infections for a given wave. Indeed, all waves prior to vaccination ended because of herd immunity—some fraction of the population had to become immune to prevent further transmission. Lockdowns did not decrease the fraction of the population that needed to become infected/immune to stop a wave. As I will show, lockdowns may even increase the required fraction of immune needed to achieve her immunity.
Reducing hospital overcapacity is the goal of lockdowns. As per the above, lockdowns cannot prevent a wave of Covid, but can reduce its peak amplitude. Keeping this peak amplitude under hospital capacity was thus the appropriate goal of lockdown policy. The meaning of hospital capacity is subsequently explored and demonstrates another domain in which economics sheds more light on pandemic planning than epidemiology alone.
Expected (and actual) vaccine development took too long for it to affect lockdown policy for a given wave of Covid. Covid waves typically lasted 6 months (even under lockdowns which are assumed to prolong waves), while vaccine development and dissemination took years. Here, the only exception might have been the final Covid wave where vaccines had been ordered and suppliers had begun to give estimated dates for delivery. This occurred most of the way through the third wave, where Covid deaths had already begun tapering.
Previously infected patients are immune. Although this wasn’t strictly true, previously infected patients were less likely to become reinfected and less likely to die once infected. Indeed, previous infection confers about as much reduction in the risk of death as vaccination, even for subsequent variants (Rick et al., 2023). As such, this model follows the Susceptible - Infected - Recovered approach. Why the R stands for recovered not removed, the importance of which will be shown. It is possible that the immunity provided by previous infection combined with reinfection made infected people socialise above the social optimum. However, very few observers considered even reinfection likely at the time—rationality is bounded by available information.
In terms of total deaths, I believe the above assumptions alone imply that the optimum Covid policy is to vary lockdown intensity to maintain a consistent level of hospitalisation. This implies that when there are few hospitalisations (which lag infections and lead deaths), lockdowns should be relaxed, and when there are many, lockdowns should be tightened. We see that this was not the case, with lockdown stringency never dropping below 40 until the end and lockdown and tightening lagging the initial exponentiation of each wave (see Figure 4). As discussed above, lockdowns cannot change the total/per-period mean number of infections. This implies that the policy decision was between high or low variance hospitalisations, not more or fewer total hospitalisations. High variance hospitalisations imply that more of the peak of each wave is above the hospital capacity threshold, leading to more deaths.
Agents update their beliefs about the harm of social contact. True outside information and network updating (such as DeGroot updating) allow agents to converge on rational outcomes (Davids et al., 2023). (I was the research assistant on the Davids’ paper.) Lockdowns are both a source of public information and, at least sometimes, a physical impediment to rational private action (by placing a homogenous cost on social contact). Once again, viewing people as rational agents is a divergence from orthodox epidemiology.
The recovered increase herd immunity and allow for labour substitution. This assumption follows Fenichel (2013) in observing that the more recovered there are in the population, the lower a susceptibles chance of coming across an infected. There is also the important labour market consideration that if the recovered are allowed to re-join the market more quickly, they can earn money for their household, reducing the incentive for the susceptible to work. They will also increase the supply of labour, bringing down short-term wages, reducing the incentive for susceptibles to work. As such, the physical restriction effect of lockdowns acted as more than just a source of information as agent-based models sometimes assumed (Davids et al., 2023). If fairness allows, lockdown levels by age would have been even more successful and might have allowed greater youth labour force participation, a crucial issue in a country with 61% youth unemployment, the highest in the world.
The above two assumptions imply that not only is high infection/hospitalisation variance bad, but that by preventing greater transmission during Covid troughs, total infections likely increased. As this was a finding in 2013, there is no reason this could not have been incorporated into Covid planning. Although Fenichel’s (2013) result does not always bind, it clearly does in the Covid context with multiple waves of infections and required herd immunity.
Hospital capacity is endogenous to the value of a statistical life in developing countries. In the developed world, surplus hospital capacity might be considered the number of empty beds. However, in the developing world, under ordinary circumstances, patients spend much less time in hospital than the healthcare optimum, as the nation simply cannot afford otherwise.4 This is triage at the healthcare system level. If every cancer patient were to be given cutting-edge cancer treatment, it would bankrupt the nation. As such, the marginal value of saving a statistical life or QALY should equal the marginal cost of saving a life.
The relevant marginal cost is opportunity cost. The big policy temptation of lockdowns is that they externalised the costs of disease prevention away from the government and onto the people, the economy. It is tempting to believe that the primary cost of Covid is the costs of treatment and thus hospital capacity must be brought to a minimum, regardless of economic cost. However, that wealth causes health–through improved standards of living, the ability to afford private healthcare, and through taxation and concomitant public healthcare–is well understood.
Moreover, income provides non-income sources of utility. Thus, the macroeconomic costs of Covid should not be underestimated. South Africa not only lost a substantial amount of GDP, our GDP per capita growth rate has never recovered, and the long-run determinants of growth have been severely impacted. For example, learners lost more than a year’s worth of learning during Covid, with unclear long-term compounding or dissipation (Ardington et al., 2021).
The above two premises imply that a Covid hospitalisation should not have been treated differently than any other hospitalisation in terms of treatment and opportunity cost. In a given year, 85000 people die of AIDS and another 56000 die of TB in South Africa. Comparatively, only 34000 people died per year of the three years of Covid. If we are to assume that no lockdowns at all would have doubled or even tripled the number of Covid deaths, we still don’t get anywhere close to treating the life of a Covid patient equal to the life of someone infected with HIV or TB. This is before considering QALYs,5 where TB and AIDS predominately kill younger people while Covid predominately killed older people. Our yearly health budget is only R259b, the lockdowns surely cost the country a very large multiple of that budget. Indeed, in just one year, South Africa’s GDP declined by R1t, although admittedly, it is hard to decompose this decline into lockdown effects and global recessionary effects. These economic trade-offs are not easy to make and not easy to justify to either the medical community or the public. But the backlash against lockdowns has been immense, with concomitant erosion of the faith in government and healthcare services. On economic, health, and political grounds, lockdowns as implemented were a disaster.
Conclusion
South Africa’s Covid policy failed three basic tests of rationality. First, the lockdowns did not minimise infection variance and thus increased the total number of those who needed to be hospitalised but could not be. Second, preventing infections during Covid troughs prevented the creation of an immune population to buffer the susceptible from the infected. Third, the economic costs were severely disproportionate to the disease burden posed by Covid. Greater consideration of the economic and behavioural aspects of public health likely would have prevented these three policy errors.
References
Alfano, V. and Ercolano, S. 2020. The Efficacy of Lockdown Against COVID-19: A Cross-Country Panel Analysis, Applied Health Economics and Health Policy, vol. 18, no. 4, 509–17.
Ardington, C., Wills, G., and Kotze, J. 2021. COVID-19 learning losses: Early grade reading in South Africa, International Journal of Educational Development, vol. 86, 102480
Davids, A., Du Rand, G., Georg, C.-P., Koziol, T., and Schasfoort, J. 2023. Social Learning in a Network Model of Covid-19, Journal of Economic Behavior & Organization, vol. 213, 271–304
Davis, J. 2020. De Beer and Others v Minister of Cooperative Governance and Traditional Affairs (21542/2020) [2020] ZAGPPHC 184; 2020 (11) BCLR 1349 (GP) (2 June 2020)
Fenichel, E. P. 2013. Economic considerations for social distancing and behavioral based policies during an epidemic, Journal of Health Economics, vol. 32, no. 2, 440–51
Hale, T., Angrist, N., Goldszmidt, R., Kira, B., Petherick, A., Phillips, T., Webster, S., Cameron-Blake, E., Hallas, L., Majumdar, S., and Tatlow, H. 2021. A global panel database of pandemic policies (Oxford COVID-19 Government Response Tracker), Nature Human Behaviour, vol. 5, no. 4, 529–38
Herby, J., Jonung, L., and Hanke, S. H. 2022. A Literature Review and Meta-Analysis of the Effects of Lockdowns on COVID-19 Mortality, Advance Access published 2022.
Rick, A.-M., Laurens, M. B., Huang, Y., Yu, C., Martin, T. C. S., Rodriguez, C. A., Rostad, C. A., Maboa, R. M., Baden, L. R., Sahly, H. M. E., Grinsztejn, B., Gray, G. E., Gay, C. L., Gilbert, P. B., et al. 2023. Risk of COVID-19 after natural infection or vaccination, eBioMedicine, vol. 96
The Economist Intelligence Unit. 2022. Democracy Index 2022, Democracy Index 2022, Available https://www.eiu.com/n/campaigns/democracy-index-2022/ (date last accessed 2 February 2024)
By irrational, I primarily mean that the lockdown measures could not have been reasonably expected to accomplish the goal of minimising Covid deaths. A second criterion I use, and will explicitly flag, is that they reduced average welfare.
There is good evidence that people with HIV under active treatment with ART did not have elevated Covid mortality risk (Dzinamarira et al., 2022). However, in South Africa, ART treatment is not universal, leading to slightly higher relative risk (ibid.). Absolute risk was mitigated by most people with HIV being younger than 45. That HIV would not be a more significant comorbidity perhaps could not have been known.
All Figures by the author.
Of course, this is also true in the developed world. Although Baumol’s cost disease does suggest the developed world is becoming less price elastic with respect to healthcare.
Using QALYs or the value of a statistical life have divergent conclusions for Covid as Covid mostly killed the elderly. This means the proportion of lives lost to QALYs lost was much lower than, say, during the AIDS pandemic.